For people with diabetes, foot problems can become serious before they are easy to notice. Smart insoles for diabetes and other remote-monitoring tools offer a way to track changes in foot temperature, pressure, and movement between clinic visits,but they are best understood as an addition to, not a replacement for, regular foot care and professional assessment.
The promising shift is from occasional checks toward more frequent information that can prompt a timely response. Research and clinical guidance support home foot-temperature monitoring for some people at high risk, while newer smart-insole systems are being studied as broader tools for monitoring the forces and signals associated with diabetic foot ulcers. Knowing what these tools can tell you, what they cannot, and how to act on an alert helps put the technology in perspective.
What smart insoles and remote monitoring can measure
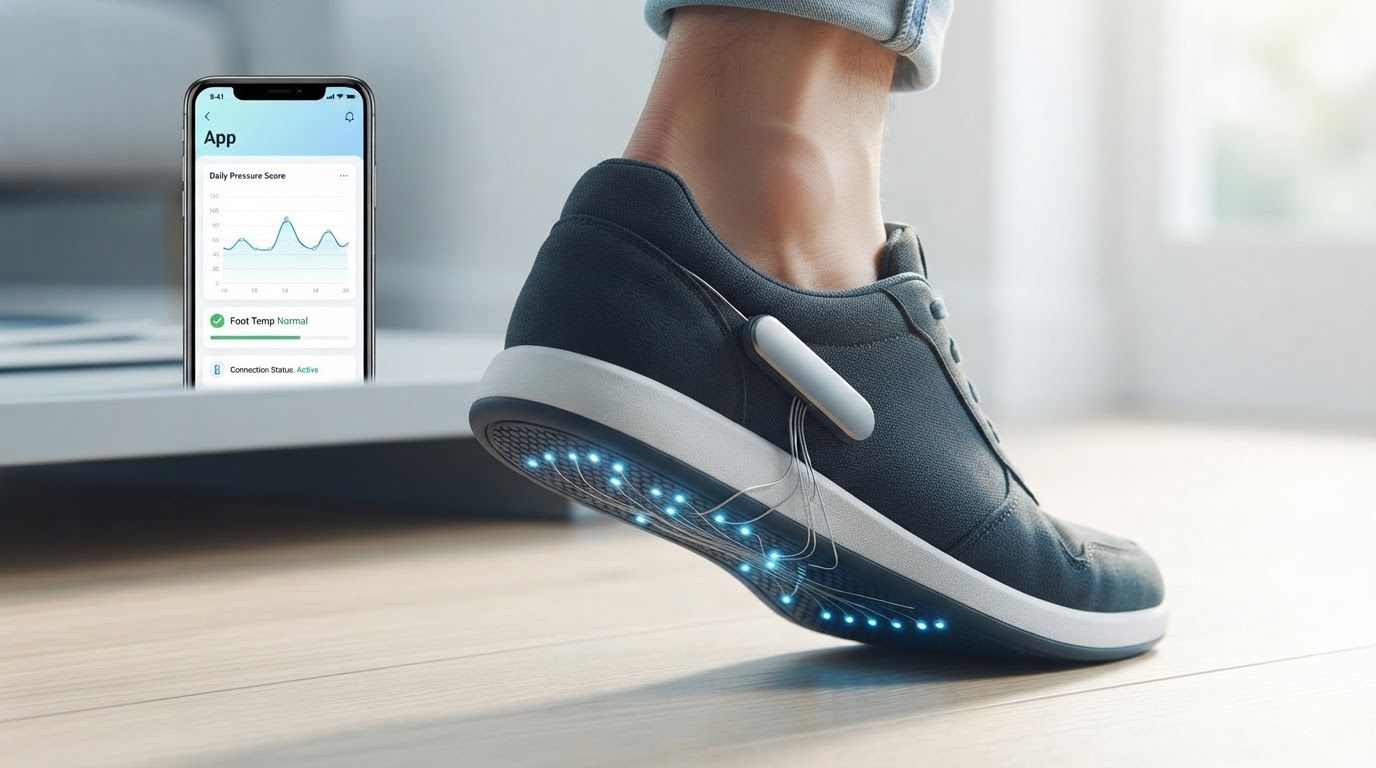
A smart insole is footwear technology that uses embedded sensors to gather information while a person stands or walks. Depending on the system, it may monitor plantar pressure,the force applied to the sole of the foot,as well as temperature, gait, loading patterns, or other biomechanical signals. Some related technologies use sensor-equipped footwear or a separate mat at home rather than an insole worn inside a shoe.
These measurements matter because diabetes-related foot risk is not limited to a visible wound. Changes in pressure or loading can indicate that particular areas of the foot are repeatedly bearing more force. Temperature monitoring can identify local differences that may be relevant to an area of concern. A wearable may collect these signals over time and send information to a person, care team, or monitoring service, depending on its design and care pathway.
Different devices answer different questions
Not every remote-monitoring product measures the same thing. A temperature mat is designed to collect foot-temperature readings at home. An insole may gather data during everyday standing or walking, including pressure and movement information. A system that measures several parameters could provide a fuller picture, but the presence of more sensors does not automatically mean a device is more accurate, useful, or suitable for every person.
Temperature monitoring looks for changes in skin temperature across foot locations. In the 2023 International Working Group on the Diabetic Foot (IWGDF) guidance, home plantar-temperature monitoring is paired with follow-up action when elevated temperatures persist for two consecutive days.
Pressure monitoring tracks how force is distributed across the sole. This can help identify loading patterns that may be relevant to risk, but the reading needs interpretation in the context of the person’s foot, footwear, activity, and clinical history.
Gait and loading measures describe aspects of how a person moves and bears weight. They can add context to pressure information, though they do not by themselves diagnose an ulcer or establish its cause.
The emerging direction is toward multi-parameter monitoring rather than a single pressure sensor. Reviews describe smart insoles as systems that may continuously collect plantar pressure, temperature, gait or loading patterns, and related biomechanical signals. That is a description of the technology’s potential, not a guarantee that every available product measures all of these signals or has been validated for every clinical purpose.
Remote monitoring also involves more than the sensor. A useful system needs a way to collect readings consistently, make the results understandable, and connect a concerning pattern to an appropriate next step. Without that response pathway, a stream of measurements may be difficult to turn into practical prevention.
How smart insoles for diabetes fit into a prevention pathway
In brief: Smart insoles and remote foot-temperature monitors collect repeated information about the foot, which may help identify changes that deserve attention. For people at high risk, IWGDF guidance supports daily home plantar-temperature monitoring with follow-up action when elevated temperatures persist for two consecutive days. These tools can support prevention, but they do not replace structured foot examinations, clinical advice, or prompt assessment of a new wound.
A prevention pathway connects measurement to action. A person uses a device as instructed, the system identifies a reading or trend of concern, and the person follows a plan agreed with their care team. That plan might include contacting a clinician or taking another recommended step. The appropriate response depends on the device, the person’s risk, and the clinical instructions they have received; an alert is not a diagnosis.
From a reading to a useful response
Collect readings consistently. Follow the device’s instructions and the monitoring schedule agreed with the care team. The IWGDF recommendation for home plantar-temperature monitoring is at least once per day for people in the relevant high-risk group.
Pay attention to a pattern, not just a number. The IWGDF guidance describes preventative action when elevated temperatures persist for two consecutive days. Do not create your own threshold or change a clinician’s plan based on a reading that the device has not explained.
Use the agreed contact route. If the system flags a concern, follow the response instructions provided by the clinical team or device service. If there is a visible wound or another urgent concern, do not wait for a wearable alert to decide whether to seek advice.
Keep routine care in place. A sensor can add information between appointments, while an in-person assessment can evaluate the skin, sensation, circulation, foot shape, and other aspects of risk.
The aim is not to make people monitor every signal without support. It is to make selected changes easier to notice and to give the person and care team a chance to respond before a small concern becomes more difficult to manage. A clear plan can also reduce uncertainty: users know what to do with a reading instead of having to interpret it alone.
Remote systems differ in how they deliver readings and alerts. Some may provide feedback directly to the user, while others may involve a monitoring service or clinical team. Before starting, ask who reviews the information, how quickly concerns are handled, and what to do if a device is unavailable or does not give a clear result. These are practical parts of the pathway, not minor technical details.
What the evidence says about remote foot monitoring
Evidence for remote monitoring includes clinical guidance, reviews of wearable technologies, and real-world studies. These forms of evidence answer different questions. Guidance summarizes evidence and recommends practice for a defined group; a review describes the state of research; and a registry can show how an intervention performs in routine use, while still leaving questions about cause and effect.
The 2023 IWGDF guideline states that, among people at high risk, home monitoring of plantar skin temperature at least once per day with preventative action when elevated temperatures persist for two consecutive days is statistically more effective than standard treatment for preventing ulcers. Its meta-analysis reported a relative risk of 0.51 for ulcer prevention with home plantar-temperature monitoring plus follow-up action. The recommendation is about a monitoring-and-response approach in a high-risk population, not about every insole or every person with diabetes.
A multicenter postmarket registry study also reported favorable outcomes among high-risk people with diabetes using remote temperature monitoring. It reported relative risk reductions of 0.68 for foot ulceration, 0.86 for moderate-to-severe ulcers, 0.83 for amputations, and 0.63 for hospitalizations. The reported numbers needed to treat (NNTs) were 5.0, 16.2, 41.7, and 5.7, respectively.
Those registry results are encouraging, but they describe associations in a real-world study. They should not be read as proof that a particular smart insole will produce the same results for every user.
Relative risk reduction is not the same as a person’s absolute chance of avoiding an outcome. The actual benefit for an individual depends on their starting risk, the monitoring approach, the actions taken in response, and the care they receive. NNTs are also tied to the study population and its circumstances; they are not a personal prediction. The registry findings provide useful evidence about remote temperature monitoring, but they do not establish that all sensor types or multi-parameter insoles have the same effects.
Feasibility matters because a monitoring tool can only help if people can and do use it. A 2026 pilot study involving 20 adults with diabetes and prior diabetic foot ulcers (DFUs) reported an average of six scans per week over six months. The intervention asked participants to stand on a mat for 20 seconds daily, and the study defined adherence pragmatically as using the mat at least four times per week. Its conclusion was that high-risk patients with diabetes can reliably engage with the technology. This is encouraging evidence about use in that small pilot, not a guarantee that every person will find every device convenient.
Further testing is under way. A randomized trial listed on ClinicalTrials.gov is designed to assess remote temperature monitoring over six to 24 months. Its outcomes include ulceration, ulcer severity, amputation, hospitalizations, emergency-room visits, quality of life, satisfaction, and self-efficacy. The intervention described in the record is a home foot-temperature mat, Podimetrics SmartMat. A trial’s planned outcomes show what researchers are evaluating; they should not be mistaken for results that have already been demonstrated.
Smart insoles, temperature mats, and standard foot care
It helps to separate three related but distinct parts of prevention: structured clinical assessment, everyday self-care, and remote sensing. Smart insoles and monitoring mats belong in the third category. They can add repeated measurements between visits, but they cannot replace the other two.
The American Diabetes Association’s 2025 Standards of Care recommend structured foot assessment that includes skin integrity, loss of protective sensation, pulses, and deformities that increase plantar pressure and ulcer risk. These checks help clinicians assess aspects of risk that a wearable reading may not capture. A device’s data may be useful to discuss during an appointment, but an examination remains important for evaluating the whole foot and the person’s clinical context.
How the tools differ in everyday use
A temperature mat may involve a brief home routine, such as standing on the mat to take readings. In the 2026 pilot described above, the instruction was to stand on the mat for 20 seconds daily. That is a study-specific instruction, not a universal requirement for every device.
A smart insole may collect readings while it is worn in footwear. Depending on the product, users may need to charge it, connect it to a phone or another receiver, or follow specific instructions about fit and use. Confirm the actual requirements before choosing a device rather than assuming all products work alike.
A clinic examination is not a sensor reading. It can assess the skin and other risk factors identified in ADA guidance, and it gives the care team a chance to put device information alongside a broader assessment.
These approaches may complement one another. For example, a person and clinician might use routine examinations to assess risk, agree on whether home monitoring is appropriate, then decide what action to take if a reading changes. The strongest practical use is not necessarily the device with the most features; it is a tool that fits the person’s routine and is linked to support they can access.
For people already managing diabetes, a wearable should not become another source of blame or pressure. A missed reading does not mean someone has failed. If a routine is difficult, tell the care team. They can help assess whether the schedule, device, or support arrangement needs to change, or whether another prevention approach is more appropriate.
Choosing a remote monitoring approach: benefits and trade-offs
There is no single best device for every person. A person with a history of DFU, a particular pattern of pressure, difficulty noticing foot changes, or other risk factors may have different needs from someone at lower risk. Device choice is a clinical and practical decision, not simply a shopping comparison based on the number of sensors.
Questions to discuss before starting
What is the device designed to measure? Ask whether it records temperature, plantar pressure, gait or loading, or a combination. Clarify which of those measures are relevant to your prevention plan.
Who is the intended user? Ask whether the evidence and instructions apply to your risk level and history. The IWGDF temperature-monitoring recommendation is specifically framed for people at high risk.
What should happen after an alert? Find out who reviews the result, how to contact the care team, and what steps you should take if a pattern is flagged. An alert without a workable response plan may create confusion rather than reassurance.
How much effort does use require? Consider whether you can manage the device’s daily or weekly routine, charging or connectivity needs, and any footwear requirements. The 2026 mat pilot shows that frequent use can be feasible for some people, but individual routines differ.
How will the information be used? Ask whether readings are shared with a clinician, stored for later review, or used to send alerts. Understand what the service does and does not monitor.
What does access cost, and is it covered? Ask the clinic or supplier about device costs and coverage. Reimbursement pathways for remote monitoring and prescription smart insoles are among the implementation issues identified in a 2026 review, so access may depend on the device and care setting.
Other trade-offs deserve a direct conversation. A wearable may make it easier to collect repeated information, but it may also require a regular routine, dependable connectivity, or comfort wearing a particular shoe or insole. Some health parameters still cannot be easily monitored at home, as acknowledged in 2026 ADA/EASD technology guidance. More information is not automatically better if it is hard to interpret or does not lead to a useful response.
Availability and clinical status also need checking. A 2026 state-of-the-art review describes smart insole systems as promising for continuous, non-invasive monitoring of foot biomechanics and physiological parameters, while discussing clinical validation, regulatory pathways, reimbursement, and barriers to prescription use. That discussion is a reminder that the field is developing: a promising technology is not necessarily a widely prescribed or universally validated standard of care.
How to make monitoring useful in daily diabetes foot care
If your care team recommends a monitoring tool, the goal is to make it fit into existing care rather than treat it as a standalone solution. Start by agreeing on the purpose: what signal is being monitored, how often to use the device, what constitutes a concern under its instructions, and whom to contact. Keep the plan somewhere easy to find, especially if family members help with care.
A practical routine to agree with your care team
Confirm your risk and the reason for monitoring. Ask how your history and foot assessment relate to the device recommendation. This helps distinguish a targeted prevention plan from general technology use.
Learn the device routine. Have the clinician or service explain setup, measurement, and any guidance for footwear or positioning. Practice until you are comfortable and know how the device signals a problem or a failed reading.
Write down the response plan. Keep the contact details and instructions close to the device. Ask what to do when an alert occurs, when a reading is unclear, or when you cannot complete the usual measurement.
Keep scheduled assessments. Continue the structured foot examinations recommended by your diabetes care team. Monitoring at home can add information between visits; it does not make those appointments unnecessary.
Review whether the routine is working. At follow-up, discuss how often you used the device, any alerts, difficulties, and whether the information changed your care. If adherence is hard, describe the reason rather than quietly abandoning the tool.
Family members can support the routine by helping with setup or remembering the agreed contact plan, if the person using the device wants that help. Support should preserve the person’s independence and preferences. It can also be useful to agree in advance who will help interpret device instructions, especially if different clinicians or services are involved.
Keep the distinction between a measurement and a diagnosis clear. A sensor may show a pattern that warrants attention, but a health professional needs to assess what it means. Conversely, the absence of an alert should not be treated as proof that there is no foot problem. Follow the device instructions and your clinician’s advice, and seek guidance about a new concern even if a monitor has not flagged it.
The best routine is one that is sustainable. The pilot that averaged six scans per week offers an example of feasibility, not a target that every user must match. If the prescribed schedule feels unrealistic, discuss it with the care team so the plan can be understood and managed. Consistency is more meaningful when the person knows why monitoring is recommended and what to do with the information.
What is changing in smart-insole research and clinical adoption
Recent reviews show that wearable technology in diabetic foot care is broadening beyond pressure measurement. A 2026 systematic review covering literature from July 2024 to May 2025 found that wearables, including smart insoles and sensor-equipped footwear, can continuously monitor plantar pressure and temperature in people at risk for diabetic foot ulcers. A separate November 2026 state-of-the-art review describes smart-insole systems as promising for continuous, non-invasive monitoring of foot biomechanics and physiological parameters, with potential applications in prevention and management.
This direction could make it possible to examine several aspects of foot loading and local conditions together, rather than relying on a single measurement. But the clinical meaning of each signal has to be established, and systems need testing in the populations and settings where they will be used. A sensor’s ability to collect data is only one step; validation must show that the data can support sound decisions and improve care.
That is why current research includes questions beyond technical performance. The 2026 review discusses clinical validation requirements, regulatory pathways, reimbursement for remote monitoring, and barriers to prescription smart insoles. These are practical issues for patients: they affect whether a device can be recommended, obtained, paid for, and integrated into a reliable care pathway.
Guidance is also beginning to recognize wearable technology as part of the wider diabetes technology conversation. The ADA/EASD 2026 technology statement notes successful use of wearables in cardiology, monitoring high-risk diabetic feet, and pediatric diabetes programs. It also cautions that some health parameters cannot yet be easily monitored at home. This balanced position reflects the opportunity and the limits: wearables can be useful in selected contexts, but they do not make every aspect of care remotely measurable.
Research on temperature mats and research on smart insoles should not be collapsed into one claim. The IWGDF recommendation and registry findings concern home plantar-temperature monitoring and a response to elevated readings. Smart insoles may capture temperature too, but they can also measure other signals, and evidence for one device type or monitoring protocol should not automatically be transferred to another. As trials report results, look for the exact technology tested, the people included, the care response used, and the outcomes measured.
Clinical trials also help clarify whether a technology works outside carefully supported settings. The randomized remote-monitoring trial described on ClinicalTrials.gov is evaluating a range of outcomes, including foot-ulcer events and quality of life. Its design illustrates why evaluation extends beyond whether a device can detect a signal: researchers also need to consider complications, healthcare use, user experience, and self-efficacy. Until those results are available, it is sensible to describe the field as promising and developing rather than settled.
Key takeaways for people considering smart foot monitoring
Smart insoles and remote temperature monitors may add a valuable layer of information for people at risk of diabetic foot complications. The strongest practical evidence in the supplied guidance supports daily home plantar-temperature monitoring, combined with follow-up action for persistent elevated readings, in high-risk people. Real-world registry results and an adherence pilot add encouragement, while ongoing trials and reviews show that broader use and validation remain active questions.
For now, the most useful next step is a conversation with your diabetes care team: ask whether your foot-risk assessment suggests monitoring, which device or approach fits your needs, and exactly what to do with an alert. Keep structured foot exams and your existing care plan in place. Technology works best when it supports attentive, informed care,not when it is expected to replace it.